Abdominal Aortic Aneurysm
An abdominal aortic aneurysm (AAA) is a permanent dilatation of the abdominal aorta, conventionally ≥30 mm. The first decision is whether it is ruptured, symptomatic or suitable for surveillance. For elective repair, balance rupture risk against procedural risk and the patient's likely benefit over their remaining life. The MDT and patient choose between open repair, endovascular aneurysm repair (EVAR) and conservative management using anatomy, physiological fitness, frailty, age, life expectancy and preferences. Diameter alone does not decide treatment. [1–3,13]
Written August 20, 2026 · Mr Razhan K Ali
1 UNDERSTAND
Describe the anatomy properly
Most AAAs are degenerative and infrarenal. Record the maximum diameter, proximal extent, neck morphology, iliac involvement and access vessels. The relationship to the renal and visceral arteries determines where an open clamp or an endovascular seal can safely sit. [1,12]
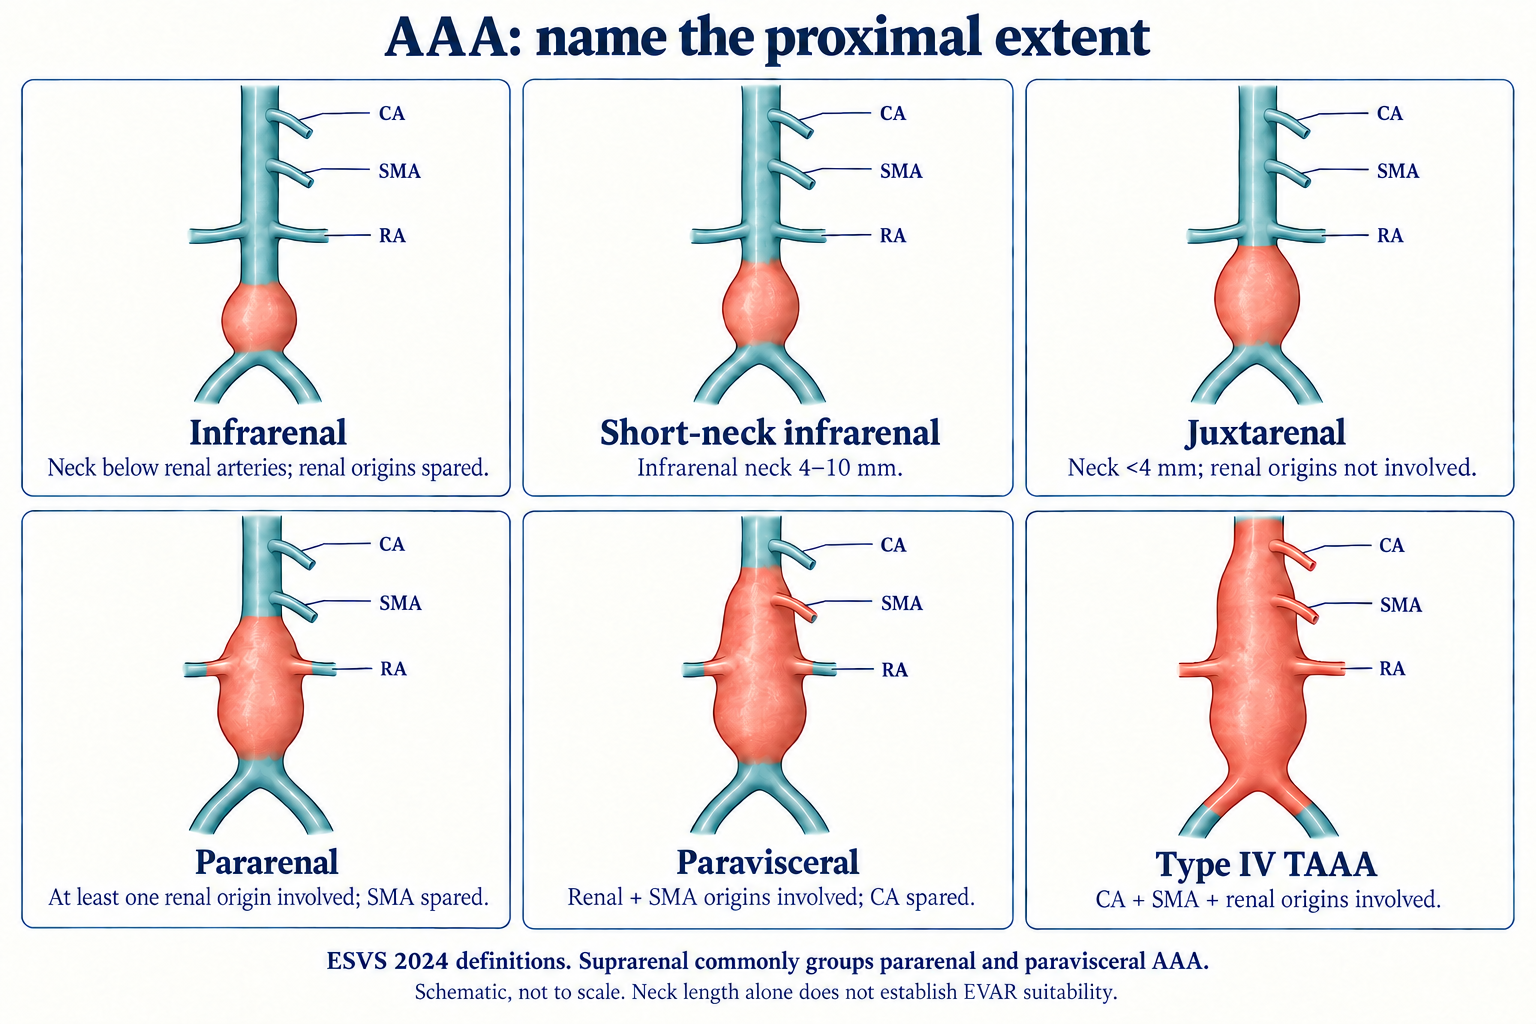
Figure 1. Proximal extent of AAA. CA = coeliac artery; SMA = superior mesenteric artery; RA = renal arteries. Coral marks the aneurysmal aortic segment and involved branch origins; colouring a branch indicates origin involvement, not necessarily aneurysmal dilatation throughout that branch. Branches are spread out for clarity; this is an original teaching schematic, not a scale drawing or a device-sizing guide. Definitions follow ESVS 2024. [1]
| Type | What it means | Why it matters |
|---|---|---|
| Infrarenal | Aneurysm below the renal arteries, with an intervening infrarenal neck. | Standard EVAR is an option only if the complete anatomy meets the chosen device's instructions for use (IFU). |
| Short-neck infrarenal | ESVS defines an infrarenal neck of 4–10 mm. | May lack a suitable seal for standard EVAR, even when an infrarenal open clamp is possible. |
| Juxtarenal | Neck <4 mm, without direct involvement of the renal artery origins. | Open repair may need clamping above one or both renal arteries; endovascular repair usually needs a more proximal seal with renal preservation. |
| Pararenal | At least one renal artery origin is involved; the SMA is spared. | Plan renal artery preservation or reconstruction. |
| Paravisceral | Renal and SMA origins are involved; the coeliac origin is spared. | Both renal and mesenteric perfusion must be preserved. |
| Suprarenal | Often used to group pararenal and paravisceral AAA. | Name the actual branch involvement rather than relying on this umbrella term. |
| Type IV thoraco-abdominal aortic aneurysm (TAAA) | Involves the abdominal aorta from the diaphragm to the bifurcation, including coeliac, SMA and renal origins. | A complex visceral-aortic repair. Other TAAA extents also involve the thoracic aorta and require their own assessment. |
These are the ESVS 2024 anatomical definitions. The treatment discussion below centres on infrarenal and complex AAA; TAAA also needs assessment through the specialist thoraco-abdominal pathway. Neck length alone does not establish EVAR suitability: diameter, angulation, thrombus, calcification, distal seals and access also matter. The aneurysm's proximal extent and the level required for an open clamp are related but are not the same classification. [1]
Describe the wall, shape and cause
-
True aneurysm: dilatation involving the arterial wall. Pseudoaneurysm: a contained wall disruption, including some anastomotic or infected lesions.
-
Fusiform: circumferential dilatation. Saccular: a focal outpouching involving part of the circumference. Exclude infection; the usual fusiform diameter threshold should not be applied automatically. Earlier treatment may be appropriate after individual assessment.
-
Inflammatory AAA: thickened wall and periaortic fibrosis, sometimes with ureteric obstruction. This changes exposure and treatment planning.
-
Infected AAA: sometimes called “mycotic”, although infection is not necessarily fungal. It requires urgent specialist assessment, microbiological investigation, antibiotics and a source-control plan; diameter is not the usual trigger for treatment. [1,12]
Presentation and investigation
Smoking, increasing age, male sex and family history are important associations. Many AAAs are incidental or screen-detected. New attributable abdominal/back pain, tenderness or embolisation makes an intact AAA symptomatic. Pain with collapse or shock raises concern for rupture; a contained rupture can initially have a normal blood pressure. [1,12]
Use ultrasound for diagnosis and surveillance. In the NHS pathway, record maximum anterior-posterior inner-to-inner diameter. Use thin-slice arterial CTA with centreline reconstructions for repair planning. Document the measurement convention and compare like with like: CT and ultrasound measurements are not interchangeable, and there is no reliable fixed conversion for an individual patient. [1–3]
For suspected rupture, activate the emergency AAA pathway immediately. Bedside ultrasound can identify an AAA but cannot reliably exclude retroperitoneal rupture. Obtain prompt CTA of the thoracoabdominal aorta and access vessels when feasible; many unstable patients can still undergo it. If the patient cannot tolerate the delay, proceed directly to theatre with the vascular and anaesthetic teams. [1]
2 DECIDE
First separate emergency, urgent and elective care
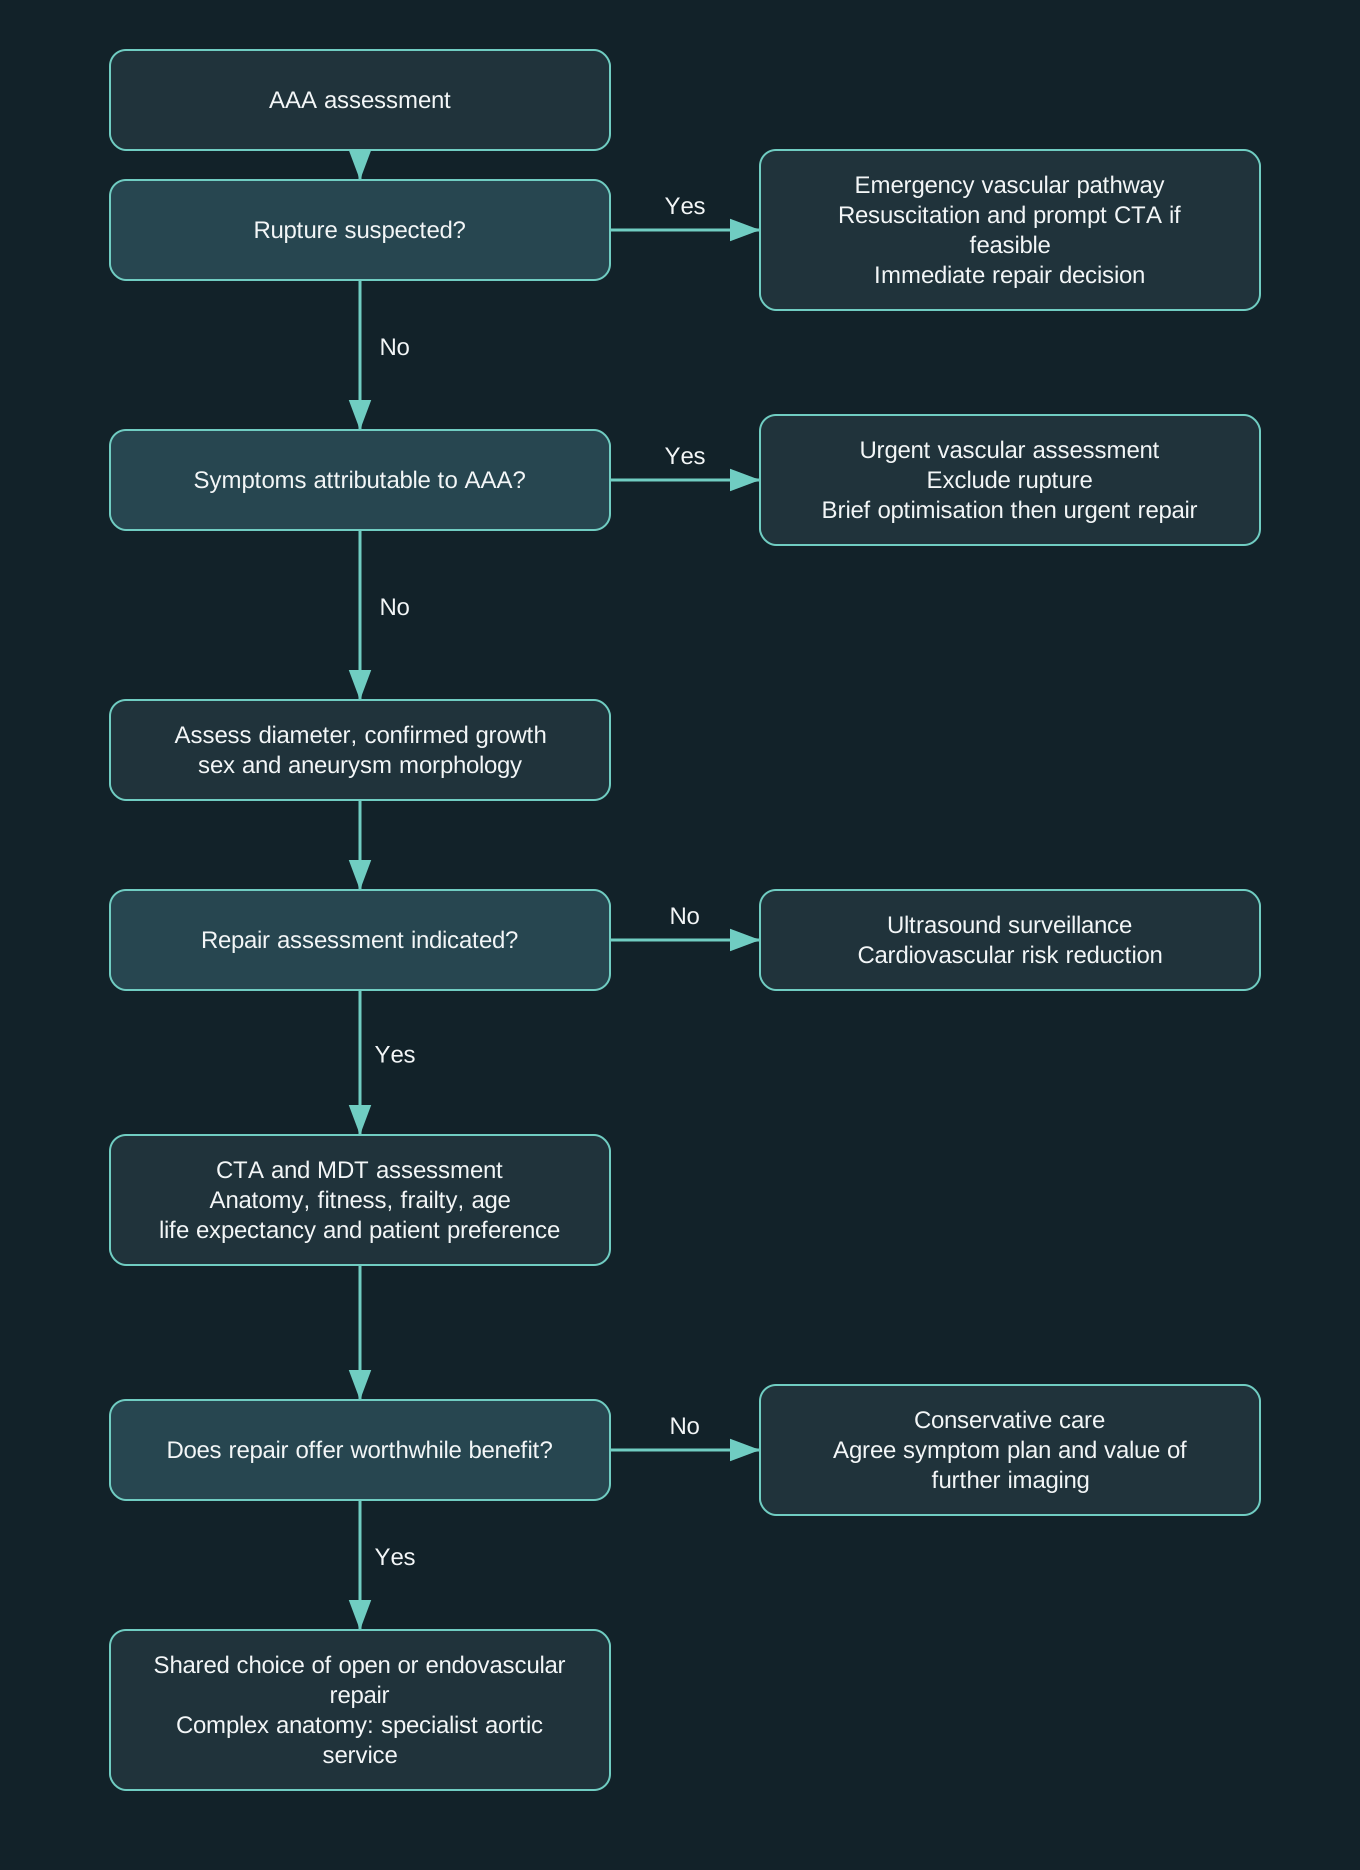
Figure 2. Clinical decision pathway. Acute symptoms override a routine surveillance appointment. The elective pathway applies to conventional degenerative AAA; infected, saccular and other atypical lesions need individual assessment. [1,2]
Rupture: activate the emergency pathway, crossmatch and use the local major-haemorrhage protocol. Avoid aggressive crystalloid loading to normalise blood pressure before haemorrhage control. Use permissive hypotension while maintaining adequate consciousness and perfusion. ESVS recommends EVAR first when anatomy is suitable; open repair remains essential when EVAR cannot be delivered safely or promptly. [1]
Symptomatic intact AAA: admit for urgent assessment. A brief period of rapid optimisation can precede urgent repair under the best available conditions. This is not routine elective surveillance. [1]
When should an asymptomatic AAA be considered for repair?
For a conventional degenerative infrarenal AAA, ESVS 2024 advises considering repair at ≥55 mm in men and allows consideration at ≥50 mm in women. The recommendation for women is weaker; this is an assessment threshold, not an automatic instruction to operate. Apparent growth of ≥10 mm/year should prompt remeasurement first, then expedited assessment if confirmed. [1]
NICE NG156 considers repair for symptoms, diameter ≥55 mm, or an asymptomatic AAA >40 mm growing >10 mm in one year, using inner-to-inner AP ultrasound measurement. It does not specify the lower female threshold used by ESVS. [2]
Complex AAA requires a separate risk calculation. ESVS permits consideration from 55 mm in men and 50 mm in women, but this is a weak recommendation based on limited evidence. Greater procedural risk may justify a higher individual threshold. Do not simply transfer the expected benefit of standard infrarenal repair to a complex visceral reconstruction. [1]
Choose the repair with the patient and MDT
Start with two questions: will repair benefit this patient, and which technically suitable option best fits their priorities? Include vascular surgery, vascular anaesthesia and the endovascular/imaging team. Assess physiological reserve, frailty, cardiac/pulmonary/renal disease, functional independence and likely survival. Age informs these judgements; it is not a standalone allocation rule. [1,13]
-
Open repair offers durable exclusion without endograft surveillance, but carries greater initial physiological stress and recovery burden. It may be attractive for a fit person with long life expectancy, or when standard EVAR anatomy is unsuitable. Laparotomy, renal, bowel, cardiac and pulmonary risks still need to be acceptable.
-
Standard EVAR generally offers lower early mortality and faster recovery in suitable patients. It requires adequate proximal/distal seals and access, adherence to IFU, and acceptance of long-term imaging and possible reinterventions. A hostile abdomen or reduced physiological reserve may make it particularly useful.
-
Complex repair needs specialist planning. Fenestrated grafts use openings aligned with branch origins; branched grafts use branch cuffs with bridging stents. They allow a more proximal seal while maintaining renal/visceral flow. Open repair uses a suitable clamp and anastomotic level, with branch reconstruction when needed. For complex AAA, ESVS supports individual choice in standard-risk patients and consideration of fenestrated/branched repair first in high surgical-risk patients. Technical feasibility alone does not establish benefit.
-
Conservative management is appropriate when repair is unlikely to improve survival or quality of life, or the patient declines it. Being unfit for open repair does not automatically make EVAR beneficial. ESVS advises against elective repair with limited life expectancy; its pragmatic example is less than about 2–3 years. [1]
Practice divergence: NICE and ESVS
ESVS, for elective asymptomatic infrarenal AAA: consider EVAR preferentially for most patients with suitable anatomy and reasonable life expectancy, while considering open repair preferentially for those with long life expectancy. Both remain individual decisions. [1]
UK guidance: NICE recommends offering open repair unless contraindicated, but explicitly allows EVAR for abdominal copathology or person-specific considerations. When open repair is contraindicated, EVAR or conservative care may be appropriate. NICE's rationale includes long-term clinical outcomes and cost-effectiveness; describing it as a cost-only decision is inaccurate. [2]
Practical interpretation: present the MDT's reasoning and the patient's choice, including early risk, durability and follow-up. For complex EVAR, NICE additionally requires discussion of outcome uncertainty, special consent/audit/research arrangements and National Vascular Registry entry. [1,2,13]
Surveillance when not repairing
Use the agreed local pathway; the NHS England programme and ESVS schedules differ. These intervals apply to asymptomatic patients who remain under surveillance, not to a symptomatic patient or someone awaiting indicated repair. [1,3]
| Pathway | Ultrasound interval |
|---|---|
| NHS England screening programme | 30–44 mm: annually. 45–54 mm: every 3 months. Refer at ≥55 mm or growth >10 mm/year. |
| ESVS: men | 30–39 mm: every 3 years. 40–49 mm: annually. ≥50 mm: every 6 months. |
| ESVS: women | 30–39 mm: every 3 years. 40–44 mm: annually. ≥45 mm: every 6 months. |
The national screening programme invites men in their 65th year; it is not a population screening programme for women. ESVS also considers five-year ultrasound follow-up for a subaneurysmal aorta of 25–29 mm. Reconsider continued surveillance if future repair would not be appropriate or wanted. [1,3]
3 JUSTIFY
Why not repair every small AAA?
UKSAT and ADAM did not demonstrate a survival advantage from routine early open repair of small asymptomatic AAAs. CAESAR and PIVOTAL likewise did not establish a survival advantage from early EVAR in their small-AAA populations. Surveillance means structured follow-up with repair when indicated. Women were underrepresented, limiting direct inference about their optimal threshold. [4–7]
Keep the evidence distinction clear: ESVS's recommendation against elective repair below 55 mm in asymptomatic men has high-level trial support. The precise threshold at which to offer repair, particularly in women or complex AAA, is less securely established. [1]
What does EVAR trade against open repair?
EVAR-1's initial report found 30-day operative mortality of 1.7% after EVAR versus 4.7% after open repair in the intention-to-treat comparison among operated patients. These historical trial rates illustrate the early advantage; use contemporary local estimates for individual consent. [8]
Long-term results need balance. EVAR-1 found higher mortality after EVAR beyond eight years, with late aneurysm-related deaths particularly associated with secondary sac rupture. In contrast, OVER's follow-up to 14 years found no significant difference in overall survival. The trials used earlier devices and practice, but they still establish why durability, reintervention and long-term surveillance belong in the initial decision. Neither “EVAR is always better” nor “open always wins long term” is supported. [9,10]
What does the rupture evidence show?
IMPROVE compared an endovascular strategy—EVAR if suitable, open if not—with an open-repair strategy in patients with suspected rupture. Thirty-day mortality was 35.4% versus 37.4%, without a statistically significant difference. It was not a simple device comparison or proof of equivalence. ESVS's current recommendation for EVAR in anatomically suitable rupture reflects the wider evidence, not a claimed positive 30-day result from IMPROVE alone. [1,11]
4 PERFORM
Prepare a plan that can actually be delivered
On CTA, review the proximal seal/clamp zone; renal and visceral origins; accessory renal arteries; maximum sac diameter; iliac aneurysm/occlusive disease; internal iliac preservation; and access calibre, calcification and tortuosity. Standard elective EVAR outside the manufacturer's IFU is not recommended by ESVS. Escalate unsuitable anatomy to the specialist aortic MDT. [1]
Optimise smoking cessation, blood pressure, lipid treatment, nutrition and functional capacity. Use cardiovascular risk-reduction therapy, including statin and appropriate antiplatelet treatment. Continue established beta-blockers; do not start them solely as routine perioperative prophylaxis. Established single antiplatelet therapy can usually continue, while anticoagulation and dual antiplatelet therapy need an individual perioperative plan, especially after recent coronary intervention. Give antibiotic prophylaxis for both open and endovascular repair. [1]
Consent should cover death, myocardial infarction, respiratory failure, renal injury/dialysis, bowel and limb ischaemia, bleeding, infection and sexual dysfunction. Add approach-specific issues: laparotomy and incisional hernia after open repair; endoleak, migration, limb occlusion, conversion, radiation/contrast exposure and repeat procedures after EVAR. Complex repair adds target-vessel failure and, particularly with more extensive aortic coverage or reconstruction, spinal cord ischaemia risk. Discuss conservative care as a real option. [1,12]
Core operative principles
Open repair: secure safe proximal and distal control, minimise renal/visceral ischaemia, replace the aneurysmal segment with a tube or bifurcated graft, and check distal and bowel perfusion. The clamp level, anastomotic level and any renal/visceral reconstruction must be planned separately. [1,12]
EVAR: obtain safe access, preserve renal and intended visceral/internal iliac flow, achieve adequate seals and component overlap, and check for endoleak, limb obstruction and access injury before completion. Fenestrated/branched repair also requires confirmation of target-vessel stent patency. [1]
Rupture: coordinate anaesthesia with readiness for proximal control; induction can precipitate cardiovascular collapse. Haemorrhage control, haemostatic resuscitation and prevention of hypothermia take priority. [1,12]
5 MANAGE
Recognise deterioration early
All open repairs and high-risk EVAR patients need immediate postoperative critical-care monitoring. Follow haemodynamics, haemoglobin, urine output, renal function, acid–base status, limb perfusion and the abdominal examination. [1]
-
Bleeding: persistent instability or falling haemoglobin needs urgent reassessment and haemorrhage control.
-
Renal injury: consider hypoperfusion, contrast exposure, embolisation and renal/bridging-stent obstruction. Suspected target-vessel occlusion requires prompt imaging and assessment for rescue.
-
Limb ischaemia: new pain, pallor, weakness or pulse loss requires urgent assessment for thrombosis, embolisation, graft-limb occlusion or access injury.
-
Colonic ischaemia: suspect it with bloody diarrhoea, abdominal pain/distension, acidosis or unexplained organ failure. Obtain urgent senior review; flexible sigmoidoscopy can assess suspected disease after rupture repair. Peritonitis or suspected transmural necrosis requires urgent operative assessment.
-
Abdominal compartment syndrome: after either open or endovascular rupture repair, monitor intra-abdominal pressure. A tense abdomen, oliguria, rising ventilatory pressures or worsening shock should trigger assessment. Established syndrome requires urgent decompression; EVAR does not remove the retroperitoneal haematoma.
-
Graft infection/aorto-enteric fistula: fever, sepsis or gastrointestinal bleeding after aortic repair warrants urgent specialist investigation. A small herald bleed can precede catastrophic haemorrhage. [1,12]
Endoleak: decide whether the sac is still at risk
Type I is failure of a proximal or distal seal; type III is component separation or fabric failure. Both need prompt assessment and reintervention to restore exclusion. Type II is retrograde filling from aortic branches: observe a stable sac; exclude occult type I/III leakage when the sac enlarges. ESVS considers intervention for type II leakage with significant sac growth ≥10 mm, measured consistently from baseline or the smallest previous diameter. [1]
Type IV is early graft porosity, now uncommon. Sac expansion with no demonstrated leak is often labelled type V/endotension; investigate for occult leak and other causes rather than assuming benign pressure transmission. A normal duplex alone does not exclude an endoleak when clinical or sac behaviour is concerning. [1,2]
Follow-up is part of the repair
-
Standard EVAR: CTA within 30 days assesses seal, overlap and endoleak. Subsequent imaging is risk-stratified. Carefully selected low-risk repairs may have less frequent imaging during the first five years; this does not mean discharge from long-term surveillance. New symptoms, sac growth or device concerns require earlier investigation.
-
Complex EVAR: CTA within 30 days and at one year, then an individual long-term programme that also assesses target vessels. Selected patients can move to duplex-based surveillance after the first year.
-
Open repair: late anastomotic and new aneurysms still occur. ESVS allows consideration of imaging the entire aorta and peripheral arteries every five years; the evidence for this interval is limited. Tailor follow-up to whether findings could lead to useful treatment. [1]
Continue cardiovascular prevention, smoking support and rehabilitation after either approach.
6 REMEMBER
-
Urgency first: rupture, symptomatic intact AAA and asymptomatic AAA are different pathways.
-
Describe the branches: juxtarenal spares renal origins; pararenal involves them; paravisceral also involves the SMA.
-
Check how it was measured: compare consistent ultrasound or CT measurements.
-
Thresholds trigger assessment: ESVS 55 mm in men, possible consideration at 50 mm in women; NICE uses 55 mm for asymptomatic size alone.
-
Confirm rapid growth before acting on a measurement difference.
-
MDT plus patient: anatomy, fitness, frailty, age, life expectancy and preference determine the plan.
-
A feasible repair may still offer no worthwhile benefit.
-
EVAR buys an early advantage with a continuing surveillance obligation. Open repair also has late complications.
-
After rupture repair, think bowel ischaemia and abdominal compartment syndrome.
-
An enlarging EVAR sac needs an explanation; type I and III leaks need prompt treatment.
-
Wanhainen A, Van Herzeele I, Bastos Gonçalves F, et al. ESVS 2024 Clinical Practice Guidelines on the Management of Abdominal Aorto-Iliac Artery Aneurysms. Eur J Vasc Endovasc Surg. 2024;67:192–331. Guideline PDF. DOI.
-
NICE. Abdominal aortic aneurysm: diagnosis and management (NG156). 2020. Recommendations. Rationale and impact.
-
NHS England. NHS abdominal aortic aneurysm screening programme: care pathway. Updated 27 October 2025. Care pathway.
-
UK Small Aneurysm Trial Participants. Mortality results for randomised controlled trial of early elective surgery or ultrasonographic surveillance for small abdominal aortic aneurysms. Lancet. 1998;352:1649–1655. Original study. DOI: 10.1016/S0140-6736(98)10137-X.
-
Lederle FA, Wilson SE, Johnson GR, et al. Immediate repair compared with surveillance of small abdominal aortic aneurysms. N Engl J Med. 2002;346:1437–1444. ADAM. DOI: 10.1056/NEJMoa012573.
-
Cao P, De Rango P, Verzini F, et al. Comparison of surveillance versus aortic endografting for small aneurysm repair (CAESAR): results from a randomised trial. Eur J Vasc Endovasc Surg. 2011;41:13–25. CAESAR. DOI: 10.1016/j.ejvs.2010.08.026.
-
Ouriel K, Clair DG, Kent KC, Zarins CK. Endovascular repair compared with surveillance for patients with small abdominal aortic aneurysms. J Vasc Surg. 2010;51:1081–1087. PIVOTAL. DOI: 10.1016/j.jvs.2009.10.113.
-
Greenhalgh RM, Brown LC, Kwong GPS, et al. Comparison of endovascular aneurysm repair with open repair in patients with abdominal aortic aneurysm (EVAR trial 1), 30-day operative mortality results: randomised controlled trial. Lancet. 2004;364:843–848. EVAR-1 early results. DOI: 10.1016/S0140-6736(04)16979-1.
-
Patel R, Sweeting MJ, Powell JT, Greenhalgh RM. Endovascular versus open repair of abdominal aortic aneurysm in 15-years' follow-up of the UK endovascular aneurysm repair trial 1 (EVAR trial 1): a randomised controlled trial. Lancet. 2016;388:2366–2374. EVAR-1 long-term results. DOI: 10.1016/S0140-6736(16)31135-7.
-
Lederle FA, Kyriakides TC, Stroupe KT, et al. Open versus Endovascular Repair of Abdominal Aortic Aneurysm. N Engl J Med. 2019;380:2126–2135. OVER long-term results. Author-institution abstract. DOI: 10.1056/NEJMoa1715955.
-
IMPROVE Trial Investigators. Endovascular or open repair strategy for ruptured abdominal aortic aneurysm: 30 day outcomes from IMPROVE randomised trial. BMJ. 2014;348:f7661. Original study. DOI: 10.1136/bmj.f7661.
-
Tambyraja AL. Peripheral and abdominal aortic aneurysms. Chapter 13 in Loftus I, Hinchliffe RJ, eds. Vascular and Endovascular Surgery: A Companion to Specialist Surgical Practice. 7th ed. Elsevier; 2024. Relevant AAA material: pp. 197–203. ISBN 9780702084621.
-
Fludder V, Pichel A. Optimising AAA Treatment Pathways. Royal College of Anaesthetists, Chapter 14 Vascular 2026. Published 28 April 2026. UK assessment and treatment pathway.